
The short answer
Plaque is a build-up of cholesterol, calcium and inflammatory cells in the artery wall. It develops slowly over many years. Many of the things that speed it up, such as smoking, high blood pressure and high cholesterol, can be treated. Not every narrowing needs a procedure, and your treatment is planned around your symptoms, your risk and your goals.
What coronary artery disease is
The coronary arteries carry blood and oxygen to the heart muscle. In coronary artery disease (CAD), plaque builds up inside the wall of these arteries.
Some plaque hardens with calcium and slowly narrows the artery. A narrowed artery may not carry enough blood when the heart works harder, for example during exercise or stress, and this can cause symptoms. Softer plaque can crack. A blood clot then forms on it and can block the artery suddenly, which causes a heart attack. Some plaques cause symptoms early, while others cause none for years.
Common symptoms
Symptoms vary. Some people notice very little, while others are limited every day.
Chest discomfort
Tightness, pressure or heaviness in the chest.
Breathlessness
Getting short of breath, especially with effort.
Tiredness
Unexplained tiredness, or being able to do less than before.
Pain elsewhere
Discomfort that spreads to the arms, neck, jaw or back.
Risk factors
Many things raise your risk of CAD, and many of them can be changed with lifestyle and treatment.
High blood pressure
Damages artery walls over time.
High cholesterol
Adds to plaque build-up.
Diabetes
Speeds up damage to the arteries.
Smoking
A major cause of artery damage.
Family history
Heart disease in close relatives at a young age.
Inactivity and weight
Too little physical activity and carrying extra weight.
How it is diagnosed
The aim is to understand both what your arteries look like and how they affect your daily life.
Your symptoms
A detailed talk about your symptoms and what you can do day to day.
Assessment
Your history, risk factors, medicines and a physical examination.
Blood tests
Cholesterol, blood sugar, kidney function and other markers of risk.
Non-invasive tests
An ECG, echocardiogram, stress test or CT coronary angiogram.
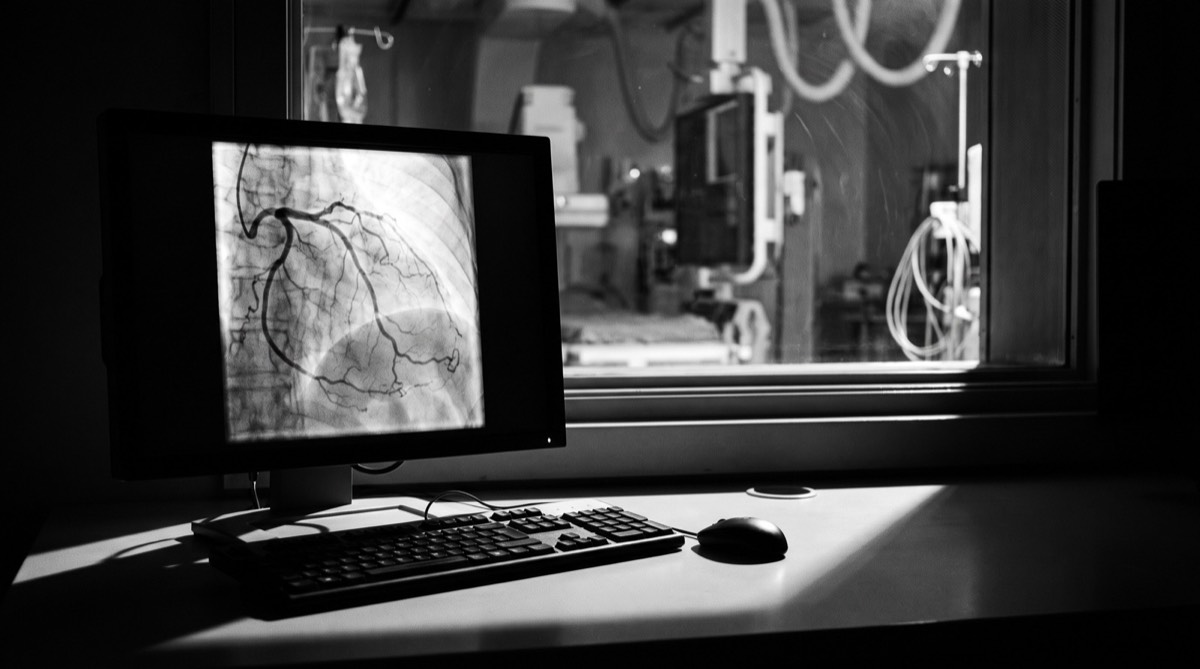
Invasive angiogram
Sometimes needed to see the arteries directly and plan treatment.
Treatment options
Most people need a combination of treatments. Not every narrowing needs a procedure.
Lifestyle changes
Healthy eating, regular activity, stopping smoking and managing stress.
Medicines
To ease symptoms, lower cholesterol, control blood pressure and reduce the chance of a heart attack.
Angioplasty and stents
A stent placed through the wrist or groin can relieve symptoms that continue despite medicines. It is also used urgently to open a blocked artery during a heart attack.
Bypass surgery
Open-heart surgery that reroutes blood around blockages. It may be recommended for extensive disease.
For some people with severe disease, bypass surgery or stents can also help them live longer. Your cardiologist will explain whether this applies to you.
What treatment aims to do
Treatment is about helping you feel better and live well, not only about opening arteries.
Ease symptoms
Less chest discomfort and breathlessness.
Improve what you can do
More exercise capacity and easier daily activities.
Lower risk
A lower chance of future heart attacks and other problems.
Quality of life
Staying active and independent.
How decisions are made
Coronary artery disease is common, and many people with it stay active, independent and well. Decisions about your care involve:
- Listening to your symptoms and concerns.
- Explaining the options clearly, including not having a procedure.
- Weighing the benefits and risks of each approach.
- Deciding together, based on your health and your goals.
For GPs
- Risk assessment: use AusCVDRisk in people aged 45–79 (30–79 for First Nations people, 35–79 with diabetes). The Heart Health Check (MBS 699) is generally for people aged 45 and over (30 and over for First Nations people); check the current MBS note for eligibility and claiming frequency.
- When to refer: exertional symptoms, a change in angina pattern, symptoms despite two anti-anginal agents, new LV dysfunction, or ischaemic ECG changes.
- Secondary prevention at diagnosis: high-intensity statin, aiming for LDL below 1.4 mmol/L and at least a 50% reduction from baseline; add ezetimibe, then a PCSK9 inhibitor if PBS criteria are met (ESC 2024 CCS; NHFA/CSANZ ACS 2025). Also antiplatelet therapy, BP control, smoking cessation, sublingual GTN and a written action plan.
- Cardiac rehabilitation: refer after ACS or revascularisation. (Cochrane 2021)
- Referral contents: symptom description, ECG, lipids, HbA1c, eGFR, AusCVDRisk score, current medicines and previous imaging reports.
General information for referring practitioners. Check current MBS and PBS criteria before acting.